
Failed IVF Cycle: 7 Critical Questions to Ask Before Trying Again
IVF did not work.
But what does “did not work” actually mean?
Was the cycle cancelled because only one or two follicles responded?
Were eggs retrieved, but many were immature?
Did very few eggs fertilise?
Did the embryos stop developing before blastocyst?
Did you transfer a good-quality embryo but receive a negative pregnancy test?
Or did implantation occur, followed by an early pregnancy loss?
These are all described casually as IVF failure.
Medically, however, they are very different situations.
After a failed IVF cycle, the most useful question is not simply:
“Why did IVF fail?”
It is:
“At which stage did the outcome start moving away from what we expected?”
That distinction matters because the next treatment plan should ideally respond to what actually happened rather than changing everything at once.

Quick answer
After a failed IVF cycle, ask your fertility specialist to review the entire treatment timeline rather than focusing only on the final pregnancy test.
Seven useful questions are:
- Where did the biggest drop-off occur?
- Was my ovarian response and egg maturity what you expected?
- What happened between fertilisation and blastocyst?
- How much did age and embryo chromosome status matter?
- If an embryo was transferred, should the uterus or transfer protocol be reviewed?
- Does the male partner need further assessment?
- Which changes proposed for the next cycle are actually supported by evidence?
One unsuccessful IVF attempt does not automatically mean that you have an implantation disorder, poor egg quality or a hidden immune problem.
Sometimes something modifiable is identified.
Sometimes the previous cycle provides information that allows the protocol to be adjusted.
And sometimes IVF simply did not succeed despite an appropriately managed cycle.
That distinction matters before deciding what to do next.v
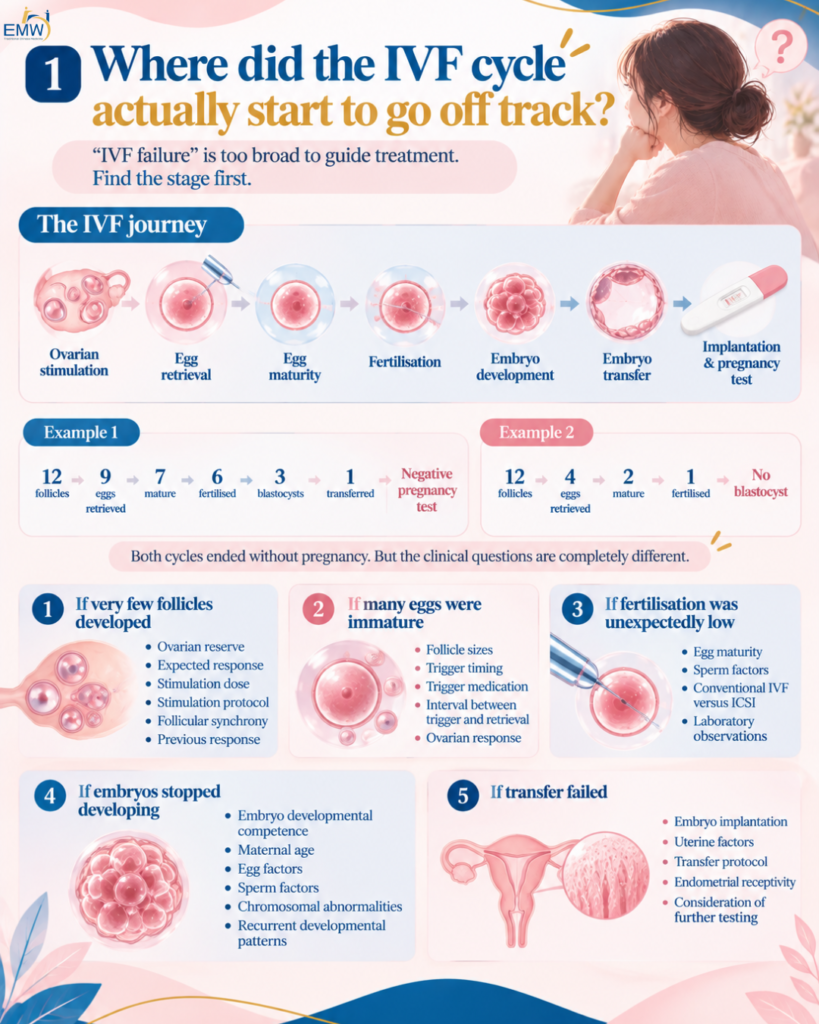
1. Where did the IVF cycle actually start to go off track?
This is the most important question.
Do not leave your IVF review with only:
“It didn’t work.”
Ask for the numbers.
A useful cycle summary might look like:
12 follicles → 9 eggs retrieved → 7 mature → 6 fertilised → 3 blastocysts → 1 transferred → negative pregnancy test
Compare that with:
12 follicles → 4 eggs retrieved → 2 mature → 1 fertilised → no blastocyst
Both cycles ended without pregnancy.
But the clinical questions are completely different.
2. Was my ovarian response actually what you expected?
The number of eggs retrieved should not be interpreted in isolation.
Ask:
How many eggs did you expect based on my AFC, AMH, age and follicle growth?
AMH and antral follicle count are useful for estimating how the ovaries may respond to stimulation and how many eggs might be retrieved.
They are much less reliable as direct measures of egg quality.
ASRM specifically notes that AMH and AFC predict egg yield considerably better than they predict pregnancy or live birth. Age remains a much stronger predictor of reproductive potential.
This distinction matters.
A woman might hear:
“Your AMH is low.”
and interpret that as:
“My eggs are poor quality.”
Those are not the same statement.
Low ovarian reserve usually means there may be fewer eggs available per stimulation cycle.
It does not tell us with certainty whether an individual egg is capable of producing a healthy embryo.

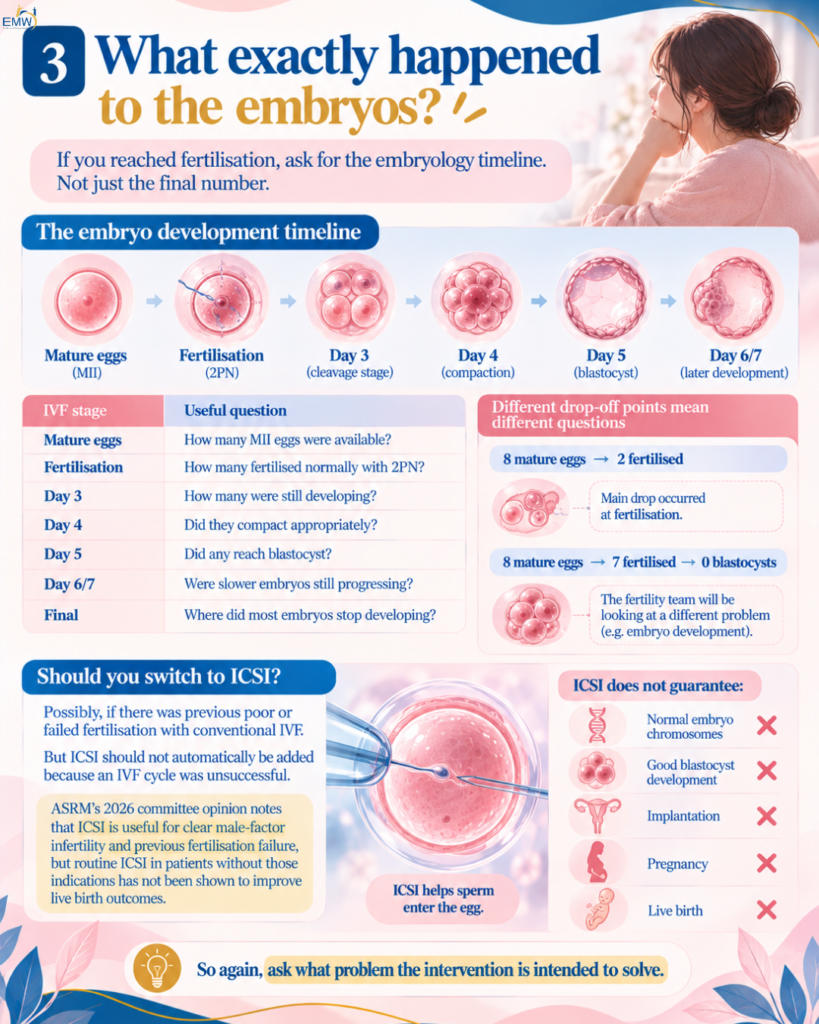
3. What exactly happened to the embryos?
If you reached fertilisation, ask for the embryology timeline.
Not just the final number.
For example:
| IVF stage | Useful question |
|---|---|
| Mature eggs | How many MII eggs were available? |
| Fertilisation | How many fertilised normally with 2PN? |
| Day 3 | How many were still developing? |
| Day 4 | Did they compact appropriately? |
| Day 5 | Did any reach blastocyst? |
| Day 6/7 | Were slower embryos still progressing? |
| Final | Where did most embryos stop developing? |
If you had:
8 mature eggs → 2 fertilised
the main drop occurred at fertilisation.
If you had:
8 mature eggs → 7 fertilised → 0 blastocysts
the fertility team will be looking at a different problem.
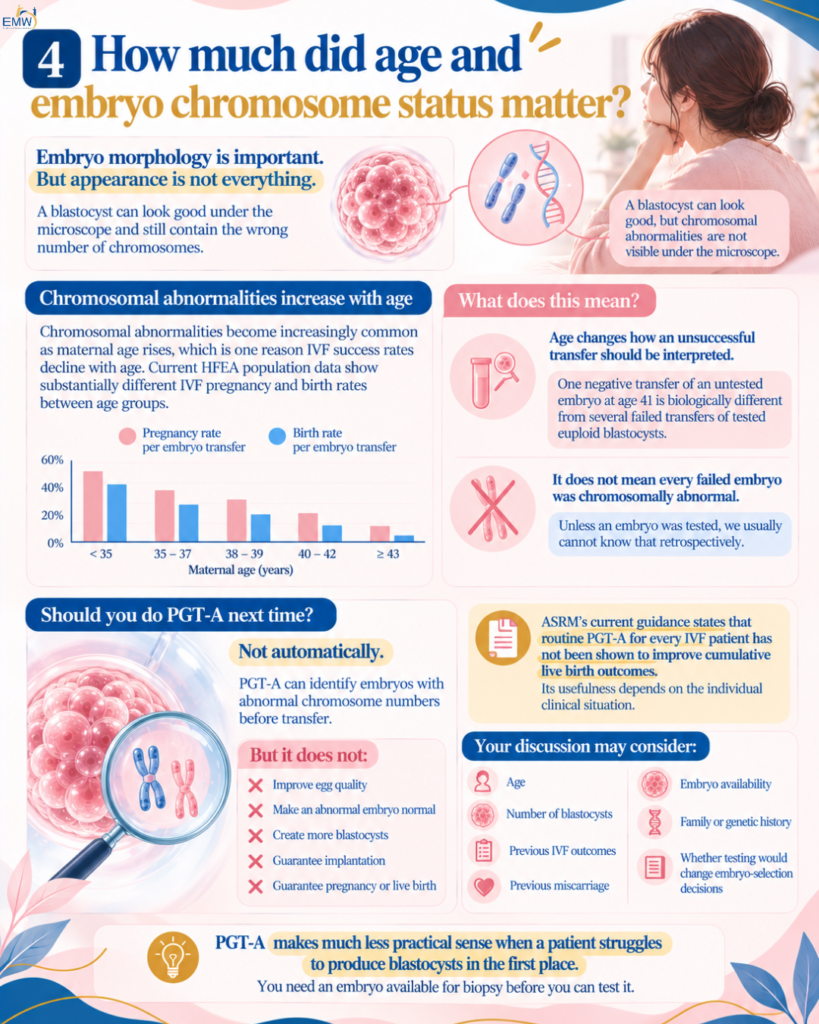
4. How much did age and embryo chromosome status matter?
Embryo morphology is important.
But appearance is not everything.
A blastocyst can look good under the microscope and still contain the wrong number of chromosomes.
Chromosomal abnormalities become increasingly common as maternal age rises, which is one reason IVF success rates decline with age. Current HFEA population data continue to show substantially different IVF pregnancy and birth rates between age groups.
That does not mean:
“Every failed embryo was chromosomally abnormal.”
Unless an embryo was tested, we usually cannot know that retrospectively.
But age changes how an unsuccessful transfer should be interpreted.
For example, one negative transfer of an untested embryo at age 41 is biologically different from several failed transfers of tested euploid blastocysts.
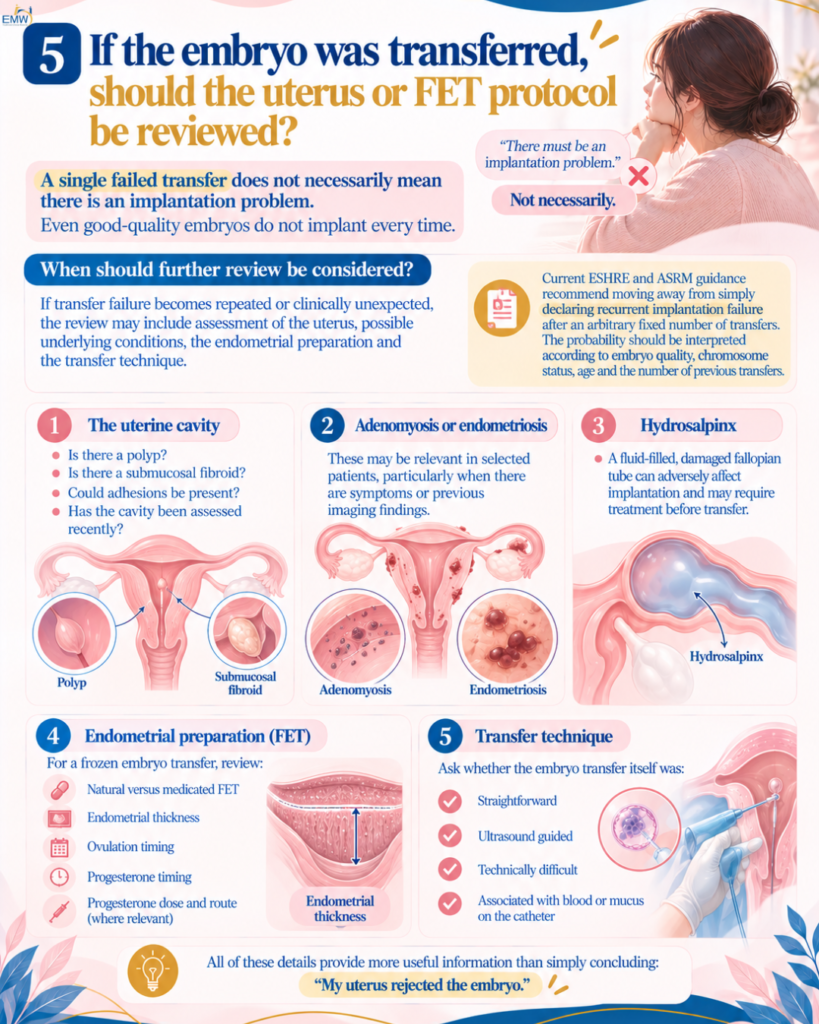
5. If the embryo was transferred, should the uterus or FET protocol be reviewed?
This is where patients often jump immediately to:
“There must be an implantation problem.”
Not necessarily.
A single failed transfer does not establish recurrent implantation failure.
Even embryos considered good quality do not implant every time.
Current ESHRE and ASRM guidance both recommend moving away from simply declaring recurrent implantation failure after an arbitrary fixed number of transfers. The probability should be interpreted according to factors such as embryo quality, embryo chromosome status, age and the number of previous transfers.
6. Should the male partner be reassessed?
Fertility treatment can become extremely female-focused.
Scans.
Injections.
Egg retrieval.
Hormones.
Embryo transfer.
Yet sperm contributes half of the embryo’s genetic material.
AUA and ASRM guidance recommends evaluation of both partners and specifically notes that male reassessment may be considered after failed assisted-reproduction cycles.
A review may include:
- previous semen analysis
- sperm concentration
- progressive motility
- morphology
- changes since the previous assessment
- fever or significant illness
- smoking or vaping
- heat exposure
- varicocele
- relevant medication
- male age
- sexual or reproductive history


7. What will actually be different next time, and why?
This is the question I would encourage every couple to ask before starting another IVF cycle.
Not:
“What else can we add?”
But:
“What did we learn, and how does that information change our plan?”
Possible changes might include:
- adjusting stimulation medication
- changing trigger strategy
- changing egg-retrieval timing
- using ICSI after previous fertilisation failure
- addressing a significant male factor
- treating uterine cavity pathology
- managing hydrosalpinx
- modifying the FET protocol
- reviewing progesterone support
- considering genetic testing in an appropriate situation
But sometimes the answer is:
“We would use essentially the same approach again.”
That is not necessarily bad medicine.
If the previous treatment was appropriate and failure can reasonably occur because IVF is probabilistic, changing everything may not improve the next outcome.
Should you take a break before another IVF cycle?
There is no universal rule.
Some patients want to begin again immediately.
Others need time.
A break does not have to mean doing nothing.
You can use the interval to:
- obtain your embryology report
- review the previous protocol
- update semen testing if needed
- address smoking
- improve sleep
- review nutrition
- maintain appropriate exercise
- correct nutritional deficiencies
- manage relevant medical conditions
- decide which proposed tests genuinely matter

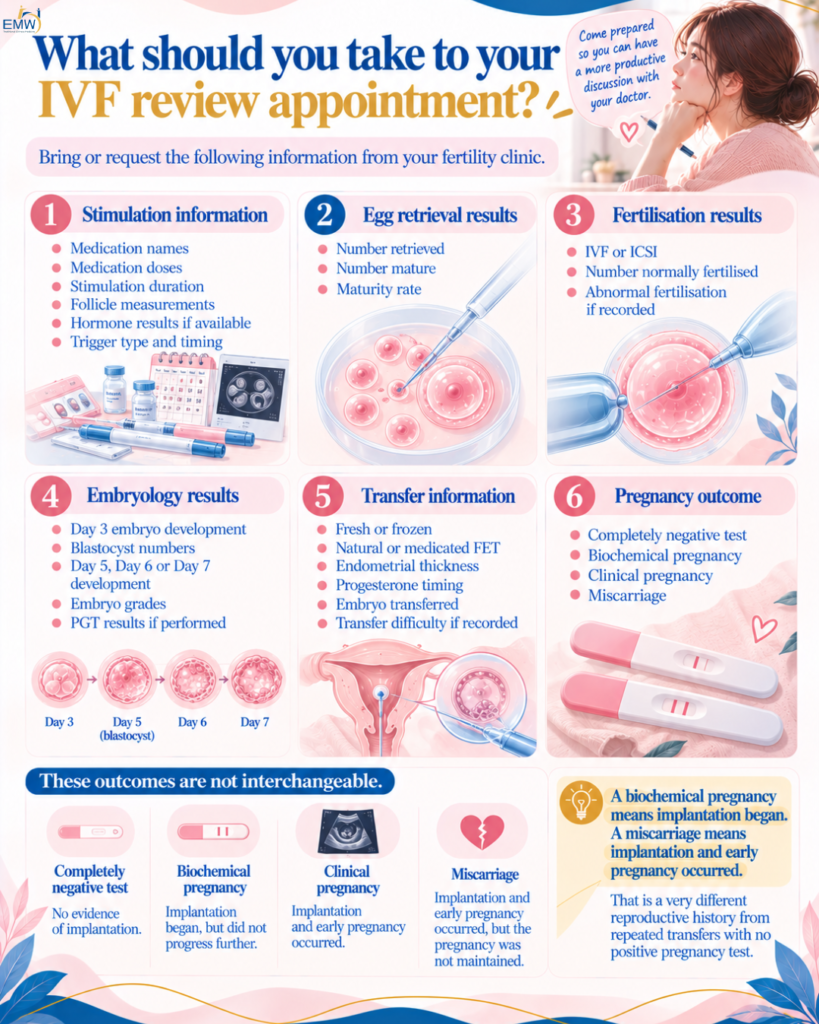
What should you take to your IVF review appointment?
Bring or request:
Stimulation information
- medication names
- medication doses
- stimulation duration
- follicle measurements
- hormone results if available
- trigger type and timing
Egg retrieval results
- number retrieved
- number mature
- maturity rate
Fertilisation results
- IVF or ICSI
- number normally fertilised
- abnormal fertilisation if recorded
Embryology results
- Day 3 embryo development
- blastocyst numbers
- Day 5, Day 6 or Day 7 development
- embryo grades
- PGT results if performed
What if the doctor says there is no clear reason?
That answer can feel deeply unsatisfying.
But sometimes it is medically accurate.
IVF does not guarantee that every competent-looking embryo will implant.
The probability of success varies with:
- age
- diagnosis
- ovarian response
- sperm
- embryo development
- chromosome status
- embryo number
- underlying medical factors
NUH similarly describes fertility treatment planning as an individualised process based on the couple’s previous reproductive history and investigations rather than one standard protocol for everybody.
Finding no obvious abnormality does not mean nobody looked properly.
And it does not automatically mean there must be a rare immune, clotting or endometrial problem waiting to be discovered.
Sometimes the next reasonable step is another properly planned cycle.

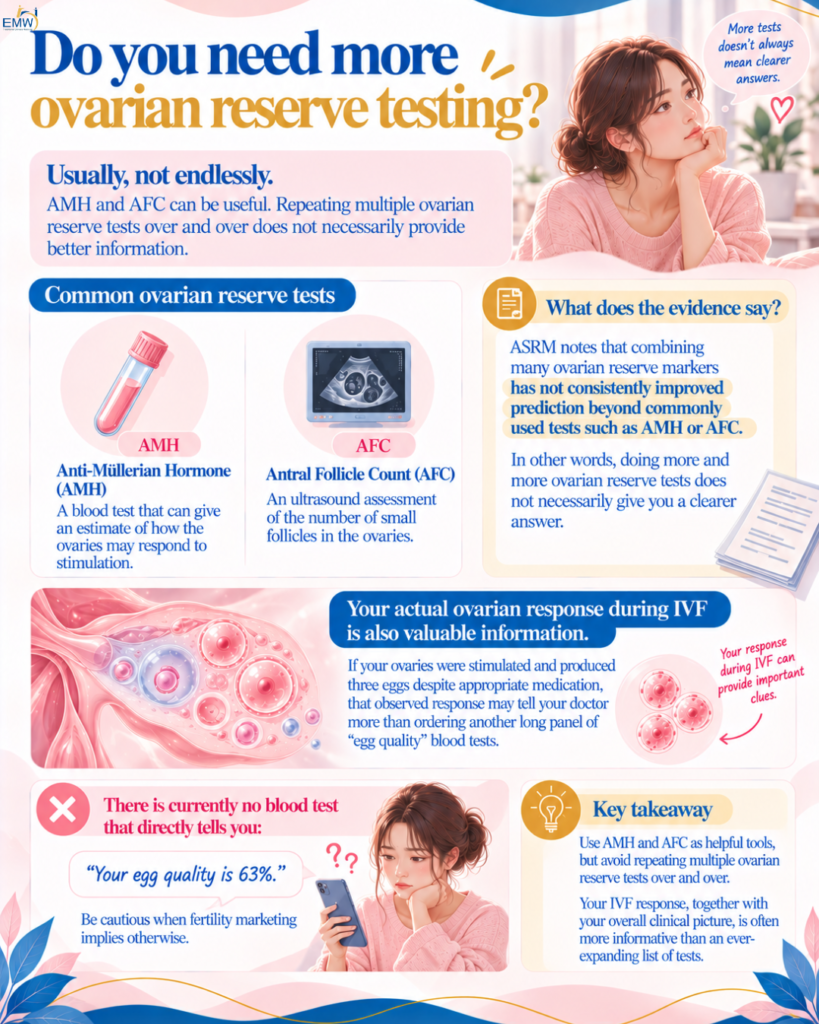
Do you need more ovarian reserve testing?
Usually, not endlessly.
AMH and AFC can be useful.
Repeating multiple ovarian reserve tests over and over does not necessarily provide better information.
ASRM notes that combining many ovarian-reserve markers has not consistently improved prediction beyond commonly used tests such as AMH or AFC.
Your actual ovarian response during IVF is itself valuable information.
If your ovaries were stimulated and produced three eggs despite appropriate medication, that observed response may tell your doctor more than ordering another long panel of “egg quality” blood tests.
There is currently no blood test that directly tells you:
“Your egg quality is 63%.”
Be cautious when fertility marketing implies otherwise.
How EMW TCM supports preparation before another IVF cycle
At EMW TCM, we see many patients after a failed IVF cycle who arrive wanting to change everything immediately.
Our first step is usually the opposite.
We try to understand what actually happened.
A fertility consultation may review:
- AMH and AFC
- previous stimulation protocol
- follicle response
- eggs retrieved
- maturity rate
- fertilisation
- blastocyst development
- embryo grading
- PGT results if available
- previous transfer protocol
- endometrial lining
- menstrual cycle
- endometriosis or adenomyosis
- sleep
- digestion
- stress
- exercise
- nutrition
- male fertility history
Our role is complementary.
Acupuncture and Chinese medicine cannot make a chromosomally abnormal embryo normal.
TCM cannot remove a significant uterine polyp, correct hydrosalpinx or substitute for appropriate male fertility assessment.
Where appropriate, TCM treatment may instead be used during the preparation period alongside conventional fertility care, with treatment adjusted according to the individual’s menstrual cycle and IVF timeline.
If you are coming for TCM support after an unsuccessful IVF attempt, bring your numbers.
They are much more helpful than simply telling us:
“The doctor said the embryos were not very good.”

EMW IVF Master Guide
Press the image to zoom in. If you like such infographics, we have a ‘3 ways to superboost your fertility’ PDF guide – Actionable steps that can help to support your reproductive health right away. You can sign up for free here: https://emwtcm.podia.com/3-ways-to-boost-your-fertility



Frequently Asked Questions
Does one unsuccessful IVF cycle mean the next one will fail too?
No.
One treatment cycle represents one ovarian response, one group of eggs and one group of embryos.
A future cycle may produce a different response and outcome.
However, repeated similar patterns become increasingly informative and should be reviewed.
Is the second IVF cycle usually more successful?
Not automatically.
The advantage of a subsequent cycle is that your fertility team now has information about how you responded previously.
That may help guide treatment, but it does not guarantee a better outcome.
Should I change IVF clinics after one unsuccessful cycle?
Not necessarily.
Start by asking for a detailed cycle review and understanding what happened.
If you have concerns about communication, laboratory performance, treatment planning or want another perspective, obtaining a second opinion is reasonable.
Should I do every available test before trying again?
Usually not.
Testing is most useful when the result has a reasonable chance of changing management.
Current professional guidance specifically cautions against indiscriminate investigation and treatment following unsuccessful embryo transfers.
Should I do PGT-A after IVF failure?
It depends.
PGT-A is not recommended as a universal solution after one unsuccessful cycle. Age, blastocyst number and reproductive history matter.
Does IVF failure mean poor egg quality?
No.
The term is too broad.
If poor embryo development occurred, egg factors may be relevant, but sperm, age, chromosomes and other biological factors may also contribute.
If a good embryo was transferred but implantation did not occur, that is a different clinical situation.
Can stress cause IVF to fail?
Feeling stressed during IVF does not mean you caused the treatment to fail.
Fertility treatment is inherently stressful.
Sleep, mental wellbeing and general health are worth supporting, but patients should not be made to believe that being anxious or having a difficult week caused an embryo not to implant.
One unsuccessful cycle can still give you valuable information
A failed IVF cycle can feel like months of injections, scans, procedures and waiting produced nothing.
But clinically, the cycle produced data.
You now know more about:
- ovarian response
- egg maturity
- fertilisation
- embryo development
- transfer
- implantation
Use that information.
Before trying again, ask:
Where did the biggest drop occur?
Was it expected?
What would you change?
Why would you change it?
What would you keep the same?
And is there evidence that the additional treatment being proposed actually improves the outcome we care about, namely having a baby?
The goal before another IVF attempt is not to add as many treatments as possible.
It is to make the next decision more informed than the last.
Preparing for your next IVF cycle?
We publish practical, evidence-informed fertility guides on IVF, FET, egg retrieval, embryo development, male fertility and natural conception.
👉 Read more on the EMW TCM Blog
If you have a few weeks or months before your next treatment cycle, our Fertility Optimisation Bundle provides structured fertility nutrition, lifestyle guidance and TCM perspectives for the preparation period.
👉 Access the Fertility Optimisation Bundle
This article is educational and does not replace advice from your fertility specialist. Always follow your IVF clinic’s instructions regarding medication, scans, trigger timing, egg retrieval, fertilisation, embryo transfer and pregnancy testing.
When to Seek Professional TCM Fertility Help
Fertility is not just a matter of age or hormones. It is a reflection of the body’s internal harmony. Traditional Chinese Medicine provides an integrative and natural way to restore this balance, supporting both physical and emotional readiness for conception.
At EMW TCM Singapore, our team of experienced physicians brings together centuries-old wisdom and modern evidence to guide your fertility journey. Whether you are trying naturally or preparing for IVF, we are here to help you create the best internal environment for new life to begin.
If you have been trying to conceive for more than six to twelve months, experience irregular menses, painful periods, or have been diagnosed with PCOS, endometriosis, or low sperm count, consider a consultation. Professional TCM fertility care aims to correct the underlying imbalance rather than simply forcing ovulation or hormone production.
Check out our links below to book your fertility consultation and begin your holistic journey toward conception.
EMW TCM Clinics
International Building Branch
360 Orchard Road, International Building #02-05/06
Singapore 238869
Book Your Appointment With Us Here: +65 89585869
Our Physicians

Principal TCM Physician
- M.Med(TCM Gynaecology)
- B.Sc(Hons) Biomedical Sciences
- Dip. Naturopath
- Ayurvedic Therapist(500hrs)
- Registered TCM Physician (Singapore MOH)

Senior TCM Physician
- M.Med(TCM Acupuncture & Moxibustion)
- B.Sc(Hons) Biomedical Sciences
- Certified Aromatherapist
- Registered TCM Physician (Singapore MOH)

TCM Physician
- M.Med(TCM Gynaecology)
- B.Sc(Hons) Biomedical Sciences
- Registered TCM Physician (Singapore MOH)

TCM Physician
- M.Med(TCM Acupuncture & Moxibustion)
- B.Sc(Hons) Biomedical Sciences
- Registered TCM Physician (Singapore MOH)

TCM Physician
- B.Med(TCM)
- B.Sc(Hons) Biomedical Sciences
- International Board-Certified Lactation Consultant (IBCLC)
- Registered TCM Physician (Singapore MOH)
References
- American Society for Reproductive Medicine. Recurrent Implantation Failure: A Committee Opinion. 2026.
- ESHRE Working Group on Recurrent Implantation Failure. ESHRE Good Practice Recommendations on Recurrent Implantation Failure. 2023.
- American Society for Reproductive Medicine. Intracytoplasmic Sperm Injection for Nonmale Factor Indications. 2026.
- American Society for Reproductive Medicine. The Use of Preimplantation Genetic Testing for Aneuploidy: A Committee Opinion. 2024.
- American Society for Reproductive Medicine. Testing and Interpreting Measures of Ovarian Reserve.
- AUA/ASRM. Diagnosis and Treatment of Infertility in Men.
- Human Fertilisation and Embryology Authority. Treatment Add-ons with Limited Evidence.
- Human Fertilisation and Embryology Authority. Statement on Fertility Treatment Add-ons. June 2026.
- National University Hospital Singapore. Reproductive Endocrinology & Infertility.